Skip to content
Glucophage
Active ingredient: Metformin

Glucophage

Quality products
24/7 Support
Fast delivery
Delivery from 4 days
Select pack Package Per unit Price

Free delivery on orders from AED 796.00, free express delivery from AED 1,194.00

Secure Payments
Track your order
Best price guarantee

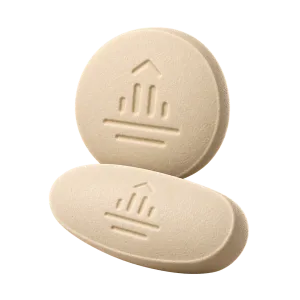
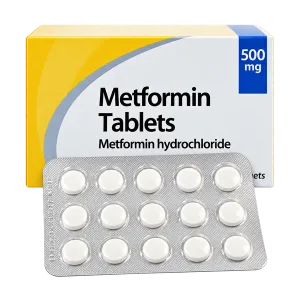
Type 2 diabetes requires sustained control of blood glucose and insulin resistance. Glucophage tablets contain metformin hydrochloride, an oral hypoglycaemic agent used mainly for adults with type 2 diabetes.

About this product

Glucophage contains metformin hydrochloride, the salt form of metformin used in oral tablets. Metformin belongs to the biguanide class of hypoglycaemic agents and is used to improve blood-glucose control in type 2 diabetes.

Pharmacological classification and active substance

Metformin hydrochloride acts mainly by reducing hepatic glucose production. It also improves insulin sensitivity in peripheral tissues, allowing muscle cells to use glucose more effectively. Unlike medicines that directly stimulate the pancreas to release insulin, metformin does not usually cause low blood glucose when used alone.

Pharmacological action

Metformin hydrochloride, the active substance in Glucophage, is a biguanide that mainly reduces hepatic glucose production. It also improves insulin sensitivity in peripheral tissues, helping muscle cells use glucose more effectively. Unlike medicines that directly stimulate pancreatic insulin release, metformin does not usually cause low blood glucose when used alone.

What it contains

Glucophage contains metformin hydrochloride, the salt form of metformin used in oral tablets. Metformin belongs to the biguanide class of hypoglycaemic agents and is used to improve blood-glucose control in type 2 diabetes. The treatment plan may include diet, physical activity, and other glucose-lowering medicines when one approach does not achieve the desired result.

Pharmacological classification and active substance

Metformin hydrochloride acts mainly by reducing hepatic glucose production. It also improves insulin sensitivity in peripheral tissues, allowing muscle cells to use glucose more effectively. Unlike medicines that directly stimulate the pancreas to release insulin, metformin does not usually cause low blood glucose when used alone.

The exact regimen for the selected Glucophage strength should be confirmed with a healthcare professional before treatment begins. The appropriate dose depends on kidney function, glucose readings, age, treatment history, and whether another diabetes medicine is being used.

Taking metformin with a meal can reduce stomach upset. Nausea is more likely when the tablet is taken on an empty stomach, especially during the first days of treatment.

Directions for use

The regimen for the chosen Glucophage strength should be confirmed with a healthcare professional before starting. The tablets are taken orally, with the frequency and amount selected according to kidney function, glucose control, tolerance, and other medicines.

Practical administration points include:

  • Take the tablet with or immediately after food if stomach upset occurs.
  • Swallow the tablet with water.
  • Use the prescribed schedule consistently.
  • If a dose is forgotten, take it when remembered unless the next dose is close.
  • Do not double the next dose to compensate for a missed dose.
  • Do not change the amount because one glucose reading is higher or lower than expected.
  • Tell the prescriber about vomiting, diarrhoea, dehydration, fever, or a planned medical procedure.

The dose may be increased gradually when gastrointestinal symptoms are significant. This approach allows the digestive system to adjust and can improve adherence. Extended-release tablets have different handling requirements from immediate-release tablets, so the formulation must be confirmed before a tablet is split or altered.

Severe vomiting or diarrhoea can cause dehydration and increase kidney stress. Contact the treating clinician promptly about whether metformin should be paused during a significant dehydrating illness.

Reasons not to use it

  • Severe renal impairment or rapidly worsening kidney function.
  • Previous lactic acidosis.
  • Severe dehydration from persistent vomiting or diarrhoea.
  • Severe infection, shock, or a condition causing reduced tissue oxygenation.
  • Significant liver disease when it increases the risk of impaired lactate clearance.
  • Known allergy to metformin hydrochloride or an excipient in the tablets.
  • Acute or unstable heart failure with poor circulation.
  • Heavy alcohol intake, which can increase metabolic stress and lactic-acidosis risk.

Kidney function should be assessed before treatment and at suitable intervals. Metformin may need to be paused around certain contrast-enhanced imaging procedures, depending on kidney function and the contrast agent used. The treating team should know about Glucophage before such a procedure.

When this is not for you

Glucophage is not suitable for everyone. It may not be for you if you have severe kidney impairment, dehydration, or a condition that raises lactic-acidosis risk. Alcohol can increase the risk of lactic acidosis, especially during fasting, dehydration, liver disease, or binge drinking. Severe symptoms after combining these factors require urgent medical attention.

Pregnancy and breastfeeding require an individual treatment decision. Diabetes itself carries pregnancy-related risks, while treatment selection depends on glucose targets and the clinical situation. The WHO diabetes guidance emphasises tailored care rather than a single regimen for every adult .

Adverse reactions

The most frequent unwanted effects involve the digestive system. Diarrhoea, nausea, abdominal discomfort, reduced appetite, bloating, and a metallic taste may occur, especially after treatment begins or after a dose increase. Taking Glucophage with food and increasing the dose gradually can help.

The FDA label identifies lactic acidosis as a rare but serious risk, with higher concern in severe kidney impairment, acute illness causing poor oxygen delivery, severe dehydration, or significant liver dysfunction . Symptoms requiring urgent medical assessment include extreme weakness, unusual sleepiness, breathing difficulty, persistent vomiting, severe abdominal discomfort, dizziness, or feeling cold.

Long-term metformin use can reduce vitamin B12 absorption in some patients. The risk is higher when treatment continues for several years, when dietary intake is low, or when symptoms such as anaemia, numbness, tingling, or a sore tongue develop. A clinician may decide to measure vitamin B12 when symptoms or risk factors are present.

One practical detail is easy to miss: diarrhoea caused by metformin can be mistaken for a food reaction. Recording the timing of symptoms in relation to each dose helps distinguish a recurring medicine effect from an isolated stomach infection. Another detail concerns appetite; reduced appetite can occur, but persistent inability to eat is not a treatment goal and may increase dehydration risk.


Uses

Glucophage is primarily used for type 2 diabetes, but its metabolic effects are broader than a single blood-glucose reading. Improved insulin sensitivity may support better fasting glucose, post-meal glucose, and glycated haemoglobin results when treatment is taken consistently and combined with an appropriate eating pattern.

Metabolic area Expected role of metformin
Liver glucose output Reduces excessive glucose release between meals
Insulin sensitivity Helps muscle and other tissues respond to insulin
Long-term glucose control Can reduce glycated haemoglobin when taken consistently

Metformin is often used as a foundation treatment because it does not usually cause weight gain and has a low risk of hypoglycaemia when taken alone. Glucophage is not a GLP-1 receptor agonist. It does not imitate GLP-1, and it does not produce the same appetite or gastric-emptying effects as GLP-1-based treatments.

Comparison

Metformin differs from other diabetes treatments through its main site of action and its effect on insulin secretion. The choice depends on kidney function, cardiovascular disease, heart failure, weight goals, hypoglycaemia risk, and the person’s ability to tolerate treatment.

Treatment approach Main action Practical limitation
Metformin Reduces hepatic glucose production and improves insulin sensitivity Gastrointestinal symptoms; kidney-related restrictions
Insulin-releasing medicines Increase pancreatic insulin secretion Greater risk of hypoglycaemia and possible weight gain
GLP-1-based treatment Enhances glucose-dependent insulin release and affects appetite and gastric emptying Nausea, injection or formulation considerations, and individual suitability

Metformin is often preferred as a first-line foundation when it is suitable. An insulin-releasing treatment may be useful when faster glucose reduction is required, yet hypoglycaemia becomes a larger concern. GLP-1-based treatment can be considered in selected patients with obesity or cardiovascular risk, but it acts through a different pathway and should not be treated as interchangeable with metformin.

Common mistakes

Several avoidable errors reduce the benefit of Glucophage:

  • Stopping after mild nausea without discussing a dose adjustment.
  • Taking extra tablets after a high glucose result.
  • Doubling the next dose after a missed tablet.
  • Continuing the medicine through severe dehydration without obtaining specific clinical instructions.
  • Crushing or chewing a modified-release tablet.
  • Forgetting to mention metformin before contrast imaging.
  • Ignoring persistent numbness, unusual tiredness, or anaemia symptoms that may warrant vitamin B12 assessment.
  • Assuming that metformin alone replaces dietary planning and glucose monitoring.

A tablet that causes repeated diarrhoea should not simply be tolerated for months. The prescriber may need to review the formulation, timing, dose escalation, kidney function, and other causes of gastrointestinal symptoms.

What doctors say

Clinicians usually judge metformin by the trend in glycated haemoglobin, fasting glucose, kidney function, and treatment tolerance rather than by one day of readings. A physician may continue it when glucose control is improving and digestive symptoms remain manageable, or adjust the plan when adverse effects interfere with meals and daily activity.

The American Diabetes Association places metformin among established glucose-lowering options, while treatment selection increasingly considers cardiovascular and kidney outcomes alongside glycated haemoglobin [1]. That approach matters because a diabetes medicine can be unsuitable even when it lowers glucose if kidney function, dehydration risk, or another medical condition changes.

Doctors also look for practical adherence problems. A person may skip tablets on busy workdays, take them without food, or stop after two days of nausea. These patterns can make a useful medicine appear ineffective. A slower dose increase, altered timing, or a different formulation may improve tolerance without abandoning metformin.

Questions and answers

What happens after stopping Glucophage, and does it need tapering?

Stopping metformin can allow blood glucose to rise again because the medicine no longer reduces hepatic glucose production or improves insulin sensitivity. NICE guidance updated in 2022 supports reviewing glucose control when diabetes treatment changes, rather than assuming that stopping is harmless. Metformin does not usually require a pharmacological taper, but the decision to stop or reduce it should be planned around glucose monitoring and the reason for discontinuation.

How soon does the effect of Glucophage become noticeable?

Some people see fasting glucose changes during the first days or weeks, while glycated haemoglobin reflects an average over a much longer period. The ADA’s 2024 Standards of Care describe glycated haemoglobin as a key measure for assessing longer-term glucose control and treatment response. Digestive side effects can appear sooner than the metabolic benefit, so early stomach discomfort does not necessarily predict the final glucose response.

Can a Glucophage tablet be split, crushed, or chewed?

Immediate-release tablets and modified-release tablets have different handling requirements. The FDA product information from 2017 states that extended-release metformin tablets should be swallowed whole and not crushed, cut, or chewed. Unless the specific Glucophage formulation has been confirmed as suitable for splitting, swallow the tablet whole with water.

How long does one dose of Glucophage keep working?

Metformin is used on a repeated schedule because its glucose-lowering effect is maintained through regular dosing rather than a single short burst. The EMA’s 2023 regulatory information for metformin medicines distinguishes formulations by release characteristics and dosing schedules. Missing doses can reduce treatment coverage, but taking extra tablets does not safely recreate the missed effect.

Do you offer anonymous delivery?

Your order will be securely packed and shipped within 24 hours. This is exactly what your package will look like (images of an actual item sent). It has the size and look of a regular private letter (24x11x0.7 cm) and its contents cannot be seen.

Comparison

Compare treatments for Diabetes

Sources

  1. American Diabetes Association (2024). Standards of Care in Diabetes—2024.

Glucophage: What Customers Say

3.8
Based on 5 reviews
Daniel, 59 Al Dhaid
Verified
Rating: 3.5 out of 5

The first week brought loose stools, but the symptoms eased after the dose was increased more slowly. After several weeks, his morning readings became more consistent.

5 Oct 2026
Huda, 39 Fujairah Three months
Verified
Rating: 3.5 out of 5

Her glucose readings improved, and she liked that she did not experience sudden low readings when using metformin alone. She still noticed a metallic taste on some mornings.

15 Oct 2026
Hamza, 49 Sharjah
Verified
Rating: 5 out of 5

He initially thought the tablets were not working. Once he stopped doubling doses and followed a regular meal-time schedule, his readings became easier to interpret.

18 Oct 2026
Lakshmi, 42 Deira Several weeks
Verified
Rating: 4 out of 5

Her stomach settled after the first fortnight, but she remained frustrated by occasional bloating. A review of timing and formulation helped reduce the problem.

28 Oct 2026
Saeed T., 40 Dubai
Verified
Rating: 3 out of 5

He felt better within days of stopping, but his glucose increased again. The experience showed him that persistent side effects required a treatment review rather than an abrupt long-term decision.

31 Oct 2026
Get our free app Shop faster and track your orders 3.8 · 441 reviews Install